
Failed IVF: What to Review Before the Next Cycle
Key Takeaways
After IVF does not work, review what happened at each step with your team. One failed transfer does not always mean something is wrong. Repeated failures or a specific finding may call for further tests or a change of plan.
Key evidence: ESHRE Good Practice Recommendations on Recurrent Implantation Failure (2023) ASRM Committee Opinion on Recurrent Implantation Failure (2026)
Failed IVF: What to Review Before the Next Cycle

A negative pregnancy test after IVF can be hard to absorb. After weeks of injections, appointments and waiting, sadness, anger or sheer exhaustion are understandable responses. The result is not evidence that you did something wrong.
It is natural to want an answer straight away, or to start another cycle as soon as possible. Yet one unsuccessful cycle rarely has a single, certain explanation. It can still provide useful clinical information. The ESHRE recommendations on recurrent implantation failure support reviewing the treatment step by step before deciding whether to repeat the plan, adjust it or pause.
The review depends on where the cycle ended. Some cycles do not reach embryo transfer; others end with a negative test after transfer. A pregnancy loss after a positive test raises different questions and may need a different assessment.
Start With a Structured Cycle Debriefing
A useful follow-up appointment looks at each stage of the cycle in turn. This is more informative than treating the result as one unexplained event:
- Ovarian stimulation and response: How many follicles grew, compared with what the team expected from your age, anti-Müllerian hormone (AMH) level and ultrasound count of small follicles?
- Egg collection and maturity: How many eggs were collected, and what percentage were mature?
- Fertilisation: Was the fertilisation rate in the expected range with conventional IVF or intracytoplasmic sperm injection (ICSI)?
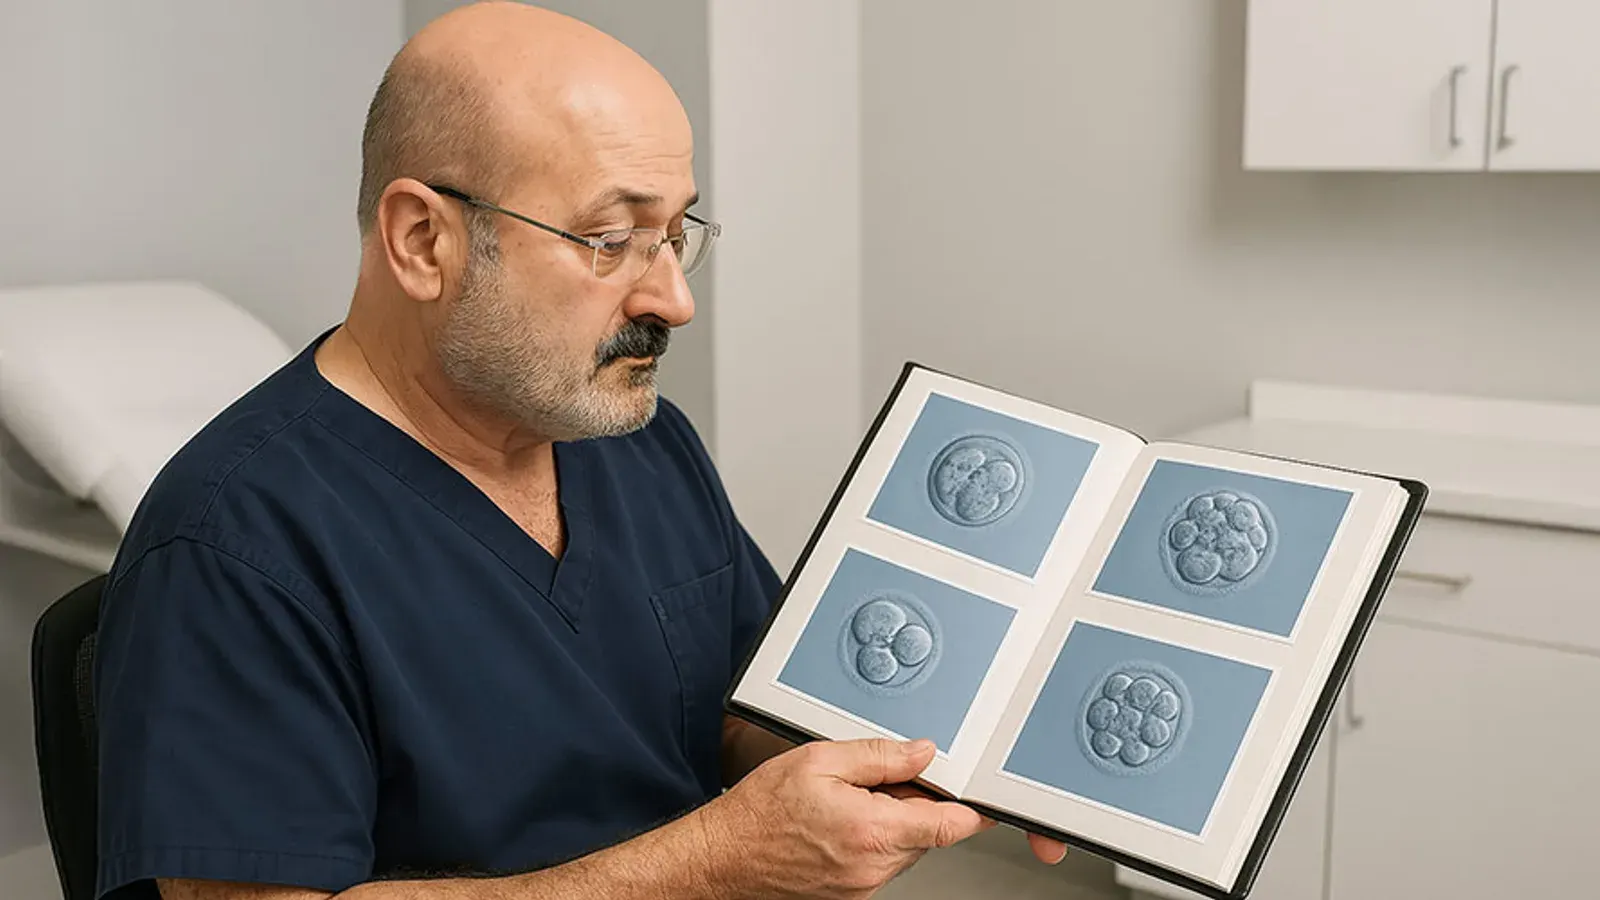
- Embryo development: Did the embryos reach the blastocyst stage, usually around Day 5 or Day 6? Which were available for transfer or freezing, and what did their grades show? If preimplantation genetic testing for aneuploidy (PGT-A) was used, how should its result be read alongside the rest of the cycle?
- Transfer and uterine factors: Was the transfer straightforward? What did the notes record about the catheter, ultrasound guidance and endometrium?
This review helps separate expected biological variation from a finding that may change the next plan.
Five Critical Questions to Ask After a Negative Result
At the follow-up appointment, five questions can help make the next step clearer.
1. Were the Ovarian Response and Trigger Timing Appropriate?
If egg yield was clearly lower than expected, the team can review the dose, medication choice and trigger timing. A very high response raises the risk of ovarian hyperstimulation syndrome (OHSS). For patients at risk, the ESHRE ovarian stimulation guideline (2025 update) recommends freezing all embryos and transferring later to minimize the risk of late-onset OHSS.
2. What Did the Laboratory Report Show?
A low fertilisation rate or an embryo that stops developing may relate to the egg, sperm or laboratory conditions. The day development stops does not by itself identify the cause. Ask the laboratory how many eggs fertilised and how the embryos developed from day to day.
3. Was the Male Partner Assessed Adequately?
Standard semen analysis assesses sperm concentration, movement and shape. For couples with failed assisted-reproduction cycles, the AUA/ASRM male infertility guideline says clinicians should evaluate the male partner (a moderate recommendation). Its commentary adds that karyotype and sperm DNA fragmentation testing should be considered in that setting. For recurrent implantation failure specifically, ASRM finds insufficient evidence to recommend sperm DNA fragmentation testing, and ESHRE does not recommend it either. The choice of tests therefore depends on the history. Recurrent pregnancy loss is a separate situation.
4. Was the Uterine Cavity Assessed Adequately?
Polyps, cavity-distorting fibroids, adhesions or a uterine septum may matter, but the appropriate test depends on the history and previous imaging.
A fluid-filled blocked tube (hydrosalpinx) can reduce implantation, pregnancy and delivery rates. The ASRM committee opinion on tubal surgery reports rates about 50% lower when a hydrosalpinx is present. For a hydrosalpinx that communicates with the uterus, it recommends considering salpingectomy or tubal occlusion before IVF. Surgery still has risks, so this is an individual decision rather than a routine response to every failed cycle.
5. Were the Endometrial Preparation and Transfer Timing Well-Matched?
For frozen embryo transfer, preparation may use a natural, stimulated or programmed cycle. There is no single best protocol for everyone: a Cochrane review found it uncertain whether one regimen is more effective or safer than another. What matters is whether the chosen plan suited the patient and whether progesterone exposure and transfer timing were aligned.
When Is Additional Testing Truly Helpful?
Further tests should answer a specific clinical question. Not every test offered after an unsuccessful cycle has been shown to help.
Selected tests may be useful when there is a repeated pattern or a clear reason for concern. The ASRM recurrent implantation failure opinion and the ESHRE recommendations discuss these options and their limits:
- Uterine-cavity assessment: Saline sonography, three-dimensional ultrasound or hysteroscopy may be considered when the history or imaging suggests a cavity problem. Routine screening hysteroscopy is not an IVF add-on for everyone.
- Parental karyotyping: ESHRE says this can be considered even though chromosomal abnormalities are uncommon. It is more likely to be offered when repeated losses, abnormal semen findings or the wider history raise concern about a chromosomal rearrangement.
- Antiphospholipid testing: ESHRE recommends it after implantation failure when there are additional risk factors for thrombophilia, and says it can be considered without them. ASRM finds too little evidence to support routine testing.
- Assessment for chronic endometritis: Endometrial biopsy with CD138 staining may be considered in selected recurrent cases, but diagnostic thresholds are not standardised and evidence that treatment improves outcomes remains limited.
By contrast, broad immune panels, receptivity tests and other unproven add-ons may add cost and anxiety without a demonstrated live-birth benefit. The ESHRE add-ons recommendations explain which tests and treatments should not be used routinely.
Single Failed Cycle vs. Recurrent Failure: How Decisions Differ
A single unsuccessful transfer and repeated implantation failure are not the same clinical situation. Keeping that distinction clear helps avoid both false reassurance and unnecessary testing.
When Repeating the Plan Makes Sense
A single failed transfer—even with a high-grade blastocyst—does not by itself point to a rare disorder. Embryo potential varies with age, embryo biology and whether the outcome is measured per transfer, per retrieval or cumulatively.
If the cycle review finds no clear problem, repeating a broadly similar plan may be reasonable. That choice should reflect age, ovarian reserve, the number and type of embryos available, treatment burden and the couple’s priorities.
When Strategy Needs to Change
A larger change to the plan may be reasonable when:
- Ovarian stimulation yielded few or immature eggs despite adequate reserve.
- Fertilisation was unexpectedly low and the laboratory review identifies a reason to change the insemination plan.
- Embryos repeatedly arrest before reaching the blastocyst stage.
- Several good-quality blastocyst transfers have not led to a positive pregnancy test. This may prompt a fresh review of the whole pathway, but a fixed number of failed transfers does not by itself mean the plan must change. For reference, the 2026 ASRM opinion defines recurrent implantation failure using an estimated 95% cumulative chance of a positive test; the number of transfers depends on factors including age and whether embryos were tested. ESHRE uses a lower reference point, a 60% cumulative predicted chance of implantation, when deciding whether to start further assessment.
- The review identifies an untreated problem involving the uterine cavity, fallopian tubes or endometrium.
Practical Steps to Prepare for Your Next Consultation
Before attending your follow-up appointment, gather your complete treatment records:
- Request the full embryology report: It should record the egg count, maturity, fertilisation rate and Day 3 or Day 5 embryo grades.
- Review the stimulation chart: Note the medication doses, hormone levels and largest follicle sizes at trigger.
- Read the transfer note: Check the catheter type, ease of entry, ultrasound guidance and endometrial thickness.
- Discuss timing, not just treatment: There is no universal rule requiring a one- or two-month delay. Recovery from complications, further tests and emotional readiness may all shape the timing.
If treatment in another country is part of your planning, our guide to IVF in Turkey for international patients explains records, travel and continuity-of-care questions to consider.
Clinical Note
When an IVF cycle does not succeed, the most important medical principle is to replace speculation with systematic analysis. A single negative result is often a statistical hurdle rather than a biological barrier.
We examine the cycle from stimulation to transfer like a chain of individual links. If one link underperformed, we modify it. If every parameter was optimal, we reassure the couple and proceed with confidence rather than subjecting them to battery testing without clear evidence.
— Dr. Senai Aksoy
Frequently Asked Questions
When an IVF cycle fails, how do you distinguish between biological variation and a problem that requires a change in treatment?
The first thing I tell my patients is that a failed IVF cycle does not necessarily mean something went wrong. Even under good laboratory conditions, with a well-developed embryo and a properly prepared uterus, pregnancy is never guaranteed.
What matters to me is understanding where in the process we encountered difficulty.
If the ovaries responded as expected, we obtained a reasonable number of mature eggs, fertilisation and embryo development were satisfactory, and the transfer was straightforward, I may recommend another attempt with a similar approach. This is particularly true after a single unsuccessful transfer of an embryo that has not undergone genetic testing. Sometimes, the outcome reflects the biological limitations of the embryo rather than a problem with the treatment.
But if I see an unexpectedly poor ovarian response, a low proportion of mature eggs, repeated fertilisation problems, embryos consistently stopping development, or difficulty achieving an adequate endometrium, I start asking different questions. These findings may justify reviewing the stimulation protocol, laboratory results, sperm factors or uterine cavity before proceeding.
Repeated unsuccessful transfers also deserve attention, particularly when the embryos have a high expected implantation potential. However, I do not use a fixed number of failures as an automatic trigger for additional tests.
My approach is to review every cycle carefully, identify anything we can realistically improve, and avoid changing treatment simply because the previous attempt failed.
I do not want to repeat the same mistake, but I also do not want to change a reasonable treatment plan just because biology did not cooperate the first time.
After a failed IVF cycle, when should a patient start the next attempt? Is there a difference between a fresh and a frozen transfer?
I do not tell my patients that they must always wait two or three months after every failed attempt. If the pregnancy test is negative and there are no complications, after a frozen embryo transfer we can often plan the next transfer in the following menstrual cycle. After a fresh transfer, I check that the ovaries have recovered, since they were recently stimulated with medication. If a new egg collection is needed, I decide based on the ultrasound findings and on how the previous treatment went.
If there is OHSS, an ovarian cyst or another health problem, a longer wait may be needed. After a biochemical pregnancy or a miscarriage, I also assess the fall in the pregnancy hormone and the patient’s overall condition.
What matters to me is not completing a specific time period, but whether the patient is medically ready for the next attempt.
After a failed cycle, do you recommend uterine “cleaning”, endometrial scratching, hysteroscopy or curettage?
No. The idea that the uterus must always be “cleaned” after a failed embryo transfer is not correct. When pregnancy does not occur, the lining of the uterus renews itself with the menstrual bleed, so routine curettage is not needed.
I do not routinely recommend endometrial scratching, a small injury to the inner lining of the uterus, because it has not been reliably shown to increase the chance of pregnancy. Hysteroscopy is a different procedure. It may be considered if ultrasound raises suspicion of a polyp, an intracavitary fibroid or adhesions, or if repeated failures mean the uterine cavity needs to be reassessed.
I do not think the uterus must necessarily be intervened upon after a failed transfer. I first look at whether there is a real problem that needs to be investigated or corrected.
Can we tell from symptoms that an IVF attempt has failed?
My patients try to interpret even the smallest symptom in the days after transfer. Breast tenderness, pelvic pain, bloating or nausea can occur in pregnancy, but they can also come from the medicines we use in treatment, such as progesterone. The absence of symptoms does not mean the transfer has failed either.
Spotting or light bleeding does not necessarily mean that pregnancy has not occurred. Not having a period is not conclusive proof of pregnancy either, since the hormones used can delay menstruation.
For this reason, rather than drawing conclusions from symptoms, I ask my patients to have the beta-hCG test on the planned day. I also specifically remind them not to stop their medicines on their own before the test. If severe pain or heavy bleeding occurs, of course they should contact their doctors without waiting for the test day.
Sources
- ESHRE Working Group on Recurrent Implantation Failure; Cimadomo D, de Los Santos MJ, Griesinger G, et al. ESHRE good practice recommendations on recurrent implantation failure. Human Reproduction Open. 2023;2023(3):hoad023. PubMed · DOI
- Practice Committee of the American Society for Reproductive Medicine. Recurrent implantation failure: a committee opinion. Fertility and Sterility. 2026;126:277-293. ASRM
- Practice Committee of the American Society for Reproductive Medicine. The use of preimplantation genetic testing for aneuploidy: a committee opinion. Fertility and Sterility. 2024;122(3):421-434. PubMed · DOI · ASRM
- Practice Committee of the American Society for Reproductive Medicine. Fertility evaluation of infertile women: a committee opinion. Fertility and Sterility. 2021;116(5):1255-1265. PubMed · DOI
- Practice Committee of the American Society for Reproductive Medicine. Role of tubal surgery in the era of assisted reproductive technology: a committee opinion. Fertility and Sterility. 2021;115(5):1143-1150. ASRM · DOI
- Brannigan RE, Hermanson L, Kaczmarek J, Kim SK, Kirkby E, Tanrikut C. Updates to male infertility: AUA/ASRM guideline (2024). Journal of Urology. 2024;212(6):789-799. PubMed · DOI
- ESHRE Guideline Group on Ovarian Stimulation; Ata B, Bosch E, Broer S, et al. ESHRE guideline: ovarian stimulation for IVF/ICSI: an update in 2025. Human Reproduction. 2026;41(4):498-514. PMC · DOI
- Ghobara T, Gelbaya TA, Ayeleke RO. Cycle regimens for endometrial preparation prior to frozen embryo transfer. Cochrane Database Syst Rev. 2025;(6):CD003414. PubMed · DOI
- Lundin K, Bentzen JG, Bozdag G, et al. Good practice recommendations on add-ons in reproductive medicine. Human Reproduction. 2023;38(11):2062-2104. PubMed · DOI
Add as a Preferred Source on Google
You can add draksoyivf.com as one of your preferred health information sources on Google.

The content has been created by Dr. Senai Aksoy and medically approved.